Navigating Irritable Bowel Syndrome: Understanding the Global Digestive Disorder and Evidence-Based Strategies for Relief

Irritable Bowel Syndrome (IBS) remains one of the most prevalent yet widely misunderstood gastrointestinal conditions affecting the global population. Recent data underscores the profound psychological and physical toll of the disorder, revealing that a significant portion of sufferers would willingly trade a decade or more of their life expectancy for an immediate and permanent cure. Academic research into patient decision-making further demonstrates that individuals grappling with severe IBS symptoms—ranging from urgent, debilitating diarrhea to persistent constipation and agonizing abdominal cramps—express a willingness to accept a one percent risk of sudden death in exchange for lasting symptomatic relief.
The condition frequently disrupts daily routines, professional productivity, and psychological well-being to such an extent that sufferers report a lower health-related quality of life than individuals diagnosed with advanced chronic pathologies, including congestive heart failure, diabetes mellitus, and end-stage renal disease. Central to this diminished quality of life is gastrointestinal-specific anxiety, a pervasive psychological state characterized by chronic worry over sudden flare-ups. This anxiety often compels patients to meticulously plan their movements around the immediate availability of clean, private restrooms, leading many to systematically avoid restaurants, social gatherings, and even public physical exercise.
Clinical Evolution and Medical Definition
Historically, the medical community lacked objective diagnostic imaging markers for IBS, such as visible inflammation, tissue damage, or structural abnormalities. In decades past, this absence of physiological pathology led many healthcare professionals to dismiss the condition as purely psychosomatic. However, contemporary gastroenterology has undergone a paradigm shift, now classifying IBS as a functional neuro-gastrointestinal disorder.
Under this modern framework, medical experts understand that the complex communication network connecting the enteric nervous system of the gastrointestinal tract and the central nervous system fails to operate optimally. Consequently, the brain transmits anomalous pain signals and disrupts standard bowel motility. Epidemiological assessments indicate that IBS affects approximately 14 percent of adults worldwide, making it the most frequently diagnosed functional digestive disorder in clinical practice.

Symptomatology and Diagnostic Complexity
The clinical presentation of IBS is notoriously heterogeneous, varying widely among patients and fluctuating unpredictably over time. Sufferers may experience alternating phases of remission lasting months or years, punctuated by severe flare-ups that persist for weeks. Symptom profiles generally encompass chronic abdominal pain, cramping, irregular bowel habits—categorized primarily as constipation-predominant (IBS-C), diarrhea-predominant (IBS-D), or mixed bowel habits (IBS-M)—alongside excessive gas, abdominal bloating, and feelings of incomplete evacuation.
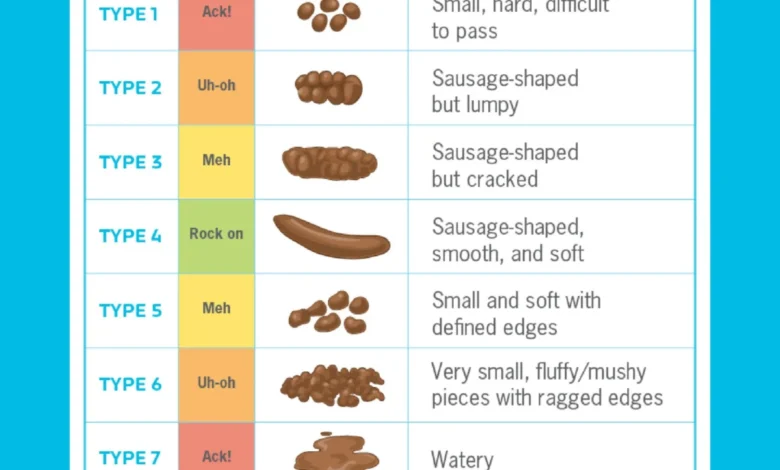
Because these symptoms frequently overlap with other serious gastrointestinal pathologies, obtaining a definitive clinical diagnosis is critical. Medical professionals must rigorously rule out inflammatory bowel diseases (such as Crohn’s disease and ulcerative colitis), celiac disease, gastrointestinal malignancies, chronic infections, and food allergies. Diagnostic protocols typically involve detailed clinical evaluations, symptom tracking via validated assessment tools such as the Bristol Stool Chart, and targeted testing to categorize the specific subtype of IBS, thereby guiding appropriate therapeutic interventions.
Etiological Theories and Physiological Mechanisms
While the exact etiology of IBS remains under active investigation, researchers have advanced several prominent hypotheses regarding its underlying mechanisms. One primary theory centers on visceral hypersensitivity, wherein the nerve endings embedded within the gastrointestinal tract exhibit an abnormally low threshold for activation. This heightened sensitivity manifests in two distinct ways: sensory nerves transmit exaggerated pain signals to the brain, causing patients to experience normal physiological processes—such as minor gas accumulation—as intensely painful; simultaneously, overactive or underactive enteric motor neurons cause gastrointestinal smooth muscle to contract erratically, driving rapid transit (diarrhea) or sluggish movement (constipation).
A secondary, highly researched theory implicates alterations in the gut microbiome. Clinical observations indicate that a substantial subset of patients develop chronic IBS symptoms following an acute gastrointestinal infection, such as Norovirus or bacterial gastroenteritis, pointing toward post-infectious microbiome dysbiosis and localized low-grade immune activation as critical contributing factors.

Multidisciplinary Management and Lifestyle Interventions
Given the multifactorial nature of the condition, current clinical guidelines advocate for a comprehensive, multidisciplinary management approach that combines medical treatments with targeted lifestyle modifications. Recent advancements by regulatory agencies, including the approval of specialized pharmacological agents and neuromodulatory medical devices, have expanded the therapeutic landscape. However, non-pharmacological lifestyle strategies remain foundational in reducing flare-ups and improving patient resilience.
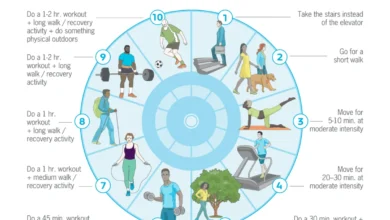
Physical activity has emerged as a robust, evidence-based intervention. Clinical studies demonstrate that regular, moderate exercise—such as brisk walking for one hour three times weekly—significantly reduces bloating and abdominal pain over a twelve-week period. Researchers hypothesize that physical activity ameliorates systemic inflammation, promotes the proliferation of beneficial gut microbiota, and enhances vagal tone, thereby optimizing gut-brain axis communication.
Simultaneously, structured stress management plays a pivotal role in symptom mitigation. Psychological stress, anxiety, and depression stimulate the hypothalamic-pituitary-adrenal axis, releasing stress hormones such as cortisol and norepinephrine that accelerate colonic transit, increase visceral sensitivity, and alter intestinal permeability. Health coaching methodologies that emphasize psychological flexibility—such as identifying elements within a patient’s sphere of control and practicing nervous system regulation techniques—have proven effective in lowering overall symptom severity.
Nutritional Strategies and Dietary Customization
Dietary management is frequently the most direct avenue for symptom control, though experts emphasize that there is no universal "IBS diet." Problematically, many patients experience severe adverse reactions to specific food categories, most notably Fermentable Oligosaccharides, Disaccharides, Monosaccharides, and Polyols (FODMAPs). These short-chain carbohydrates are poorly absorbed in the small intestine, drawing water into the lumen and undergoing rapid bacterial fermentation, which produces distension and gas.

In addition to high-FODMAP foods, common dietary triggers include caffeinated beverages, alcohol, spicy foods, high-fructose corn syrup, artificial sweeteners, and high-fat meals. To accurately identify individual sensitivities without imposing unnecessary nutritional restrictions, clinical dietitians frequently utilize structured elimination diets. These protocols typically involve the temporary removal of suspected trigger foods for a period of two to four weeks, followed by the systematic, individual reintroduction of each food item to establish precise tolerance thresholds. For complex cases, particularly those involving a strict low-FODMAP protocol, guidance from a certified specialist or registered dietitian is strongly advised to maintain nutritional adequacy.
The Role of Allied Health Coaching and Scope of Practice
As the understanding of functional gastrointestinal disorders evolves, allied health professionals and certified health coaches are increasingly integrated into the patient care continuum. Experts in the field stress the importance of maintaining a strict scope of practice: health coaches provide valuable behavioral support, assist in implementing lifestyle modifications, and guide clients through self-monitoring protocols like food and symptom diaries. However, coaches do not diagnose medical conditions, prescribe restrictive diets, or countermand medical directives. Instead, the most successful outcomes stem from a collaborative model where medical practitioners oversee clinical diagnosis and pharmacotherapy, while health and lifestyle coaches empower patients to maintain sustainable, long-term habits that improve their overall quality of life.