Navigating the Post-Pandemic Landscape: Comprehensive Tracking of Medicaid and CHIP Enrollment Trends and Unwinding Renewal Outcomes Through 2026

The American healthcare landscape has undergone profound systemic shifts since the onset of the COVID-19 pandemic, driven heavily by sweeping policy changes, fluctuating enrollment counts, and the massive administrative undertaking known as the Medicaid "unwinding." According to the latest monthly enrollment and performance indicator data compiled by the Centers for Medicare & Medicaid Services (CMS) and analyzed by health policy organizations like KFF, the national public health insurance portfolio continues to stabilize following years of unprecedented volatility. At the same time, new federal budgetary mandates are poised to reshape eligibility and participation metrics over the coming decade.
This comprehensive overview examines historical and current trends in Medicaid and the Children’s Health Insurance Program (CHIP), looks back at the critical lessons and outcomes of the post-pandemic unwinding period, and explores the looming policy implications of the 2025 federal budget reconciliation law.

Current Enrollment Trends and Post-Pandemic Baseline
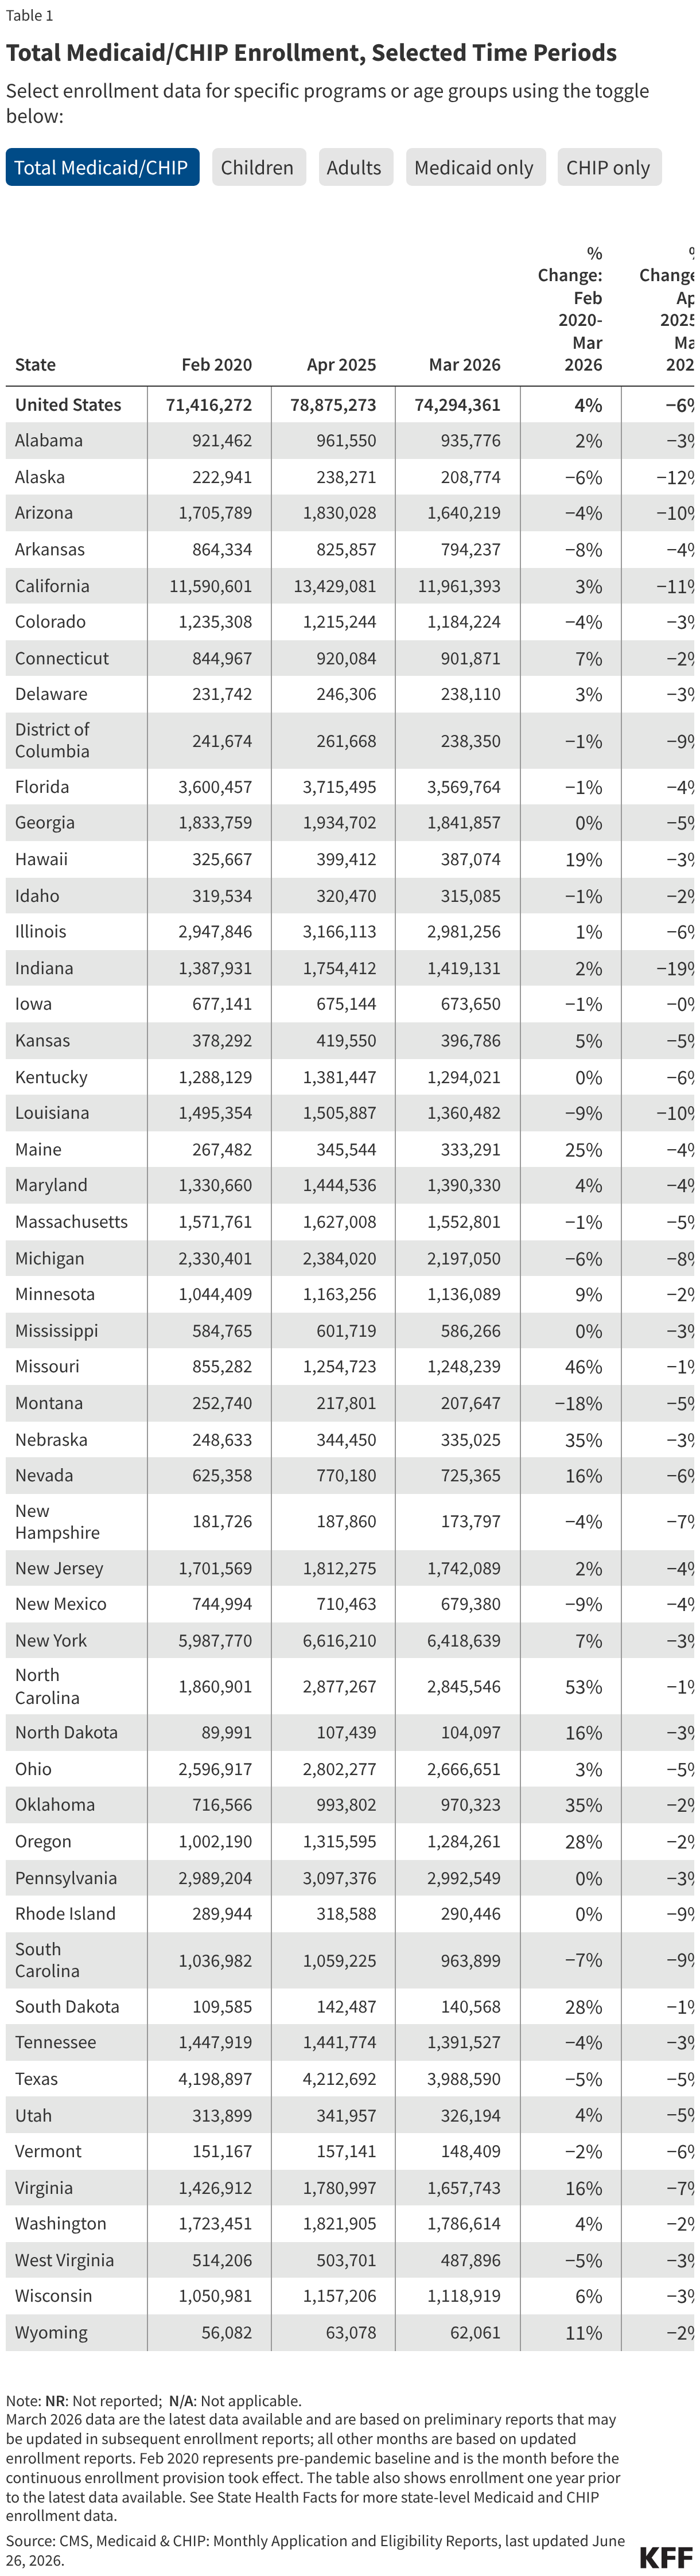
To understand where public health insurance enrollment stands as of mid-2026, it is essential to look back at the baseline established in February 2020. That month served as the final pre-pandemic benchmark, occurring just before the passage of the Families First Coronavirus Response Act (FFCRA). The FFCRA famously tied federal emergency relief funds to a "continuous enrollment" provision, which prohibited states from disenrolling individuals from Medicaid during the public health emergency, even if their financial or household circumstances changed.
This continuous enrollment guarantee caused total Medicaid and CHIP enrollment to skyrocket to historic highs, providing vital health coverage security to tens of millions of Americans during an economic crisis. However, once the continuous enrollment requirement officially expired—with states resuming normal eligibility redeterminations and disenrollments beginning at various points in 2023—enrollment figures experienced a sharp downward correction.
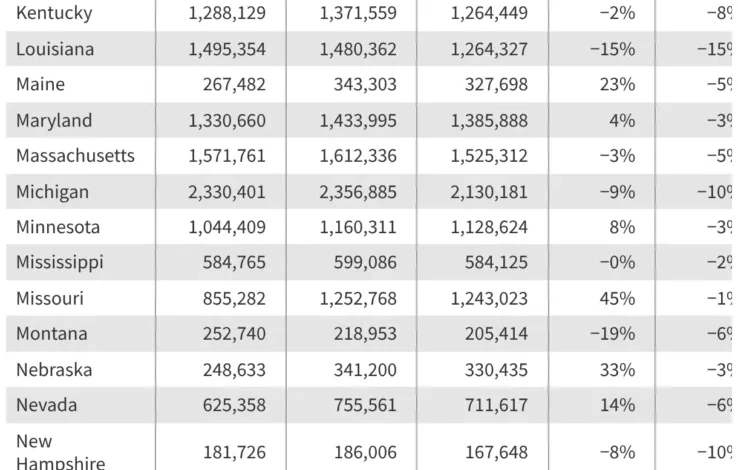
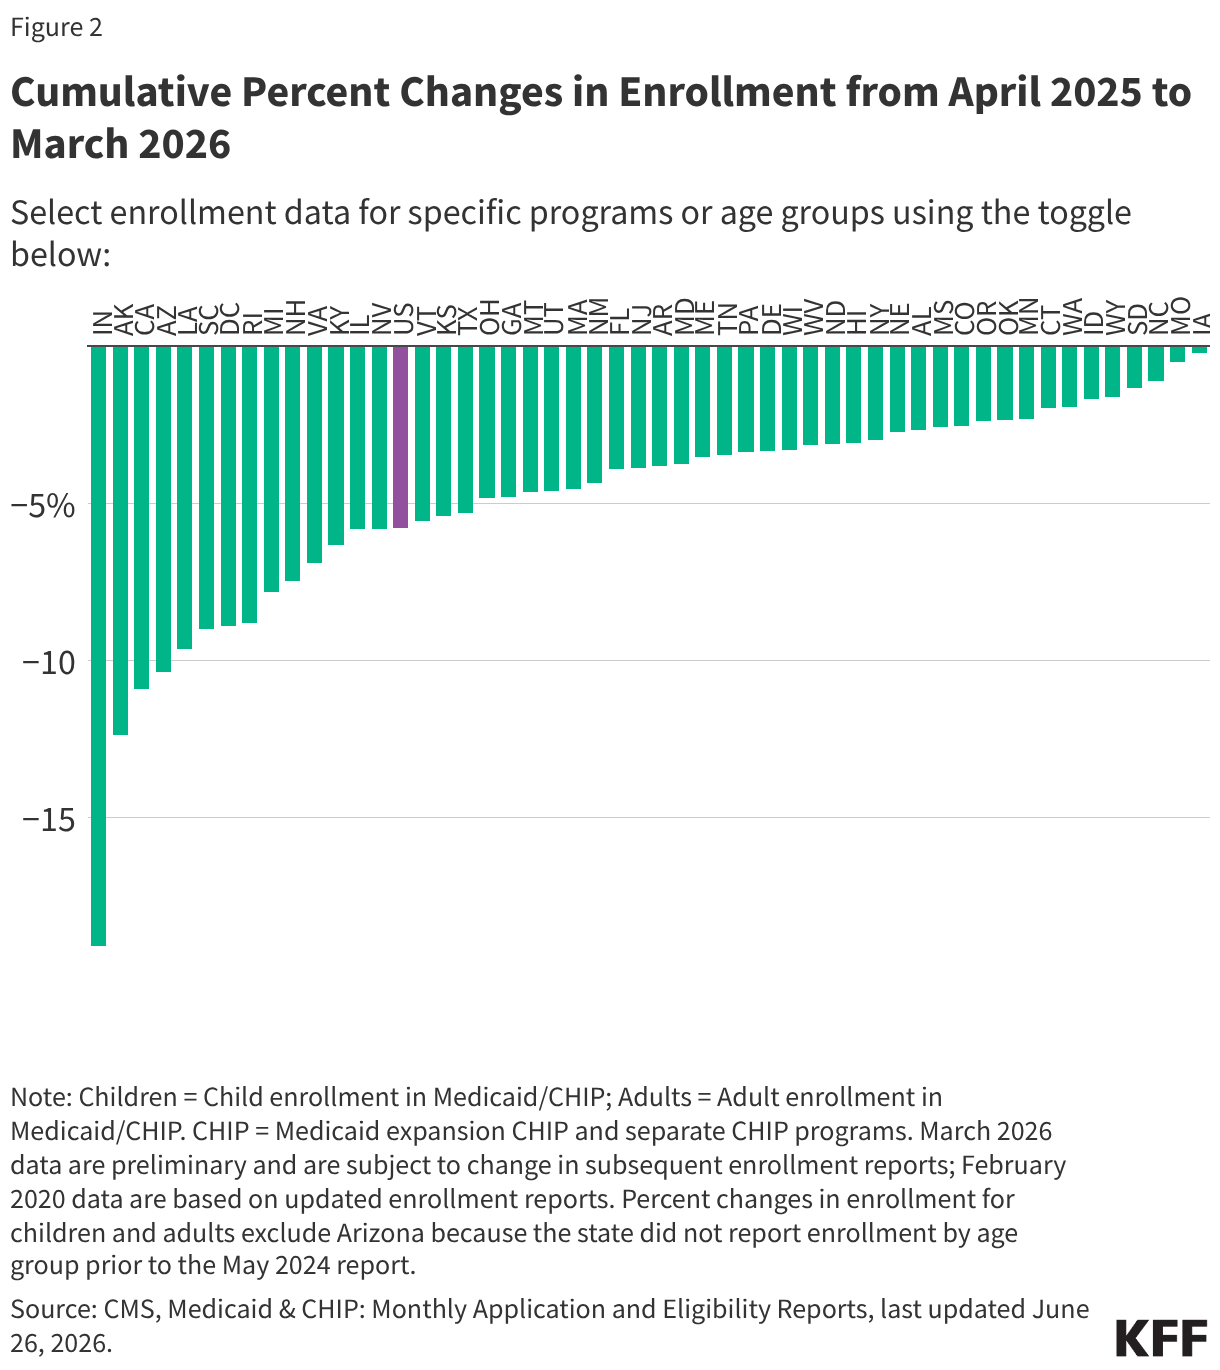
By June 2026, preliminary monthly reports from CMS indicate that the national Medicaid and CHIP landscape has found a new post-unwinding equilibrium. The data accounts for full-benefit enrollees across diverse demographic segments, including adults and children. It is important to note, however, that these specific monthly performance indicator counts omit individuals receiving limited benefits, such as those qualifying solely for family planning services. Consequently, while these indicators provide an accurate temperature check on broad national trends, they do not capture the absolute total of every individual touching the Medicaid ecosystem.
The 2025 Reconciliation Law and Future Enrollment Pressures
While the immediate shock of the post-pandemic unwinding has largely subsided, federal policy changes threaten to alter future enrollment trajectories significantly. The passage of the 2025 federal budget reconciliation law introduced major legislative overhauls to the Medicaid program. Most notably, the law mandates that non-disabled adults in the Medicaid expansion group, as well as participants in certain Section 1115 demonstration waiver programs, satisfy rigorous new work and reporting requirements beginning in January 2027.
Health policy analysts project that these mandatory work hurdles will suppress Medicaid enrollment over the next ten years compared to projections under prior law. Because failure to document compliance—even for individuals who are legally working or exempt—frequently leads to administrative disenrollments, states are bracing for another wave of coverage losses. The implementation of these work requirements is being closely monitored by researchers, and state-by-state variations are expected to highlight stark geographic disparities in how safety-net programs absorb federal regulatory changes.
Anatomy of the Medicaid Unwinding: A Retrospective Analysis
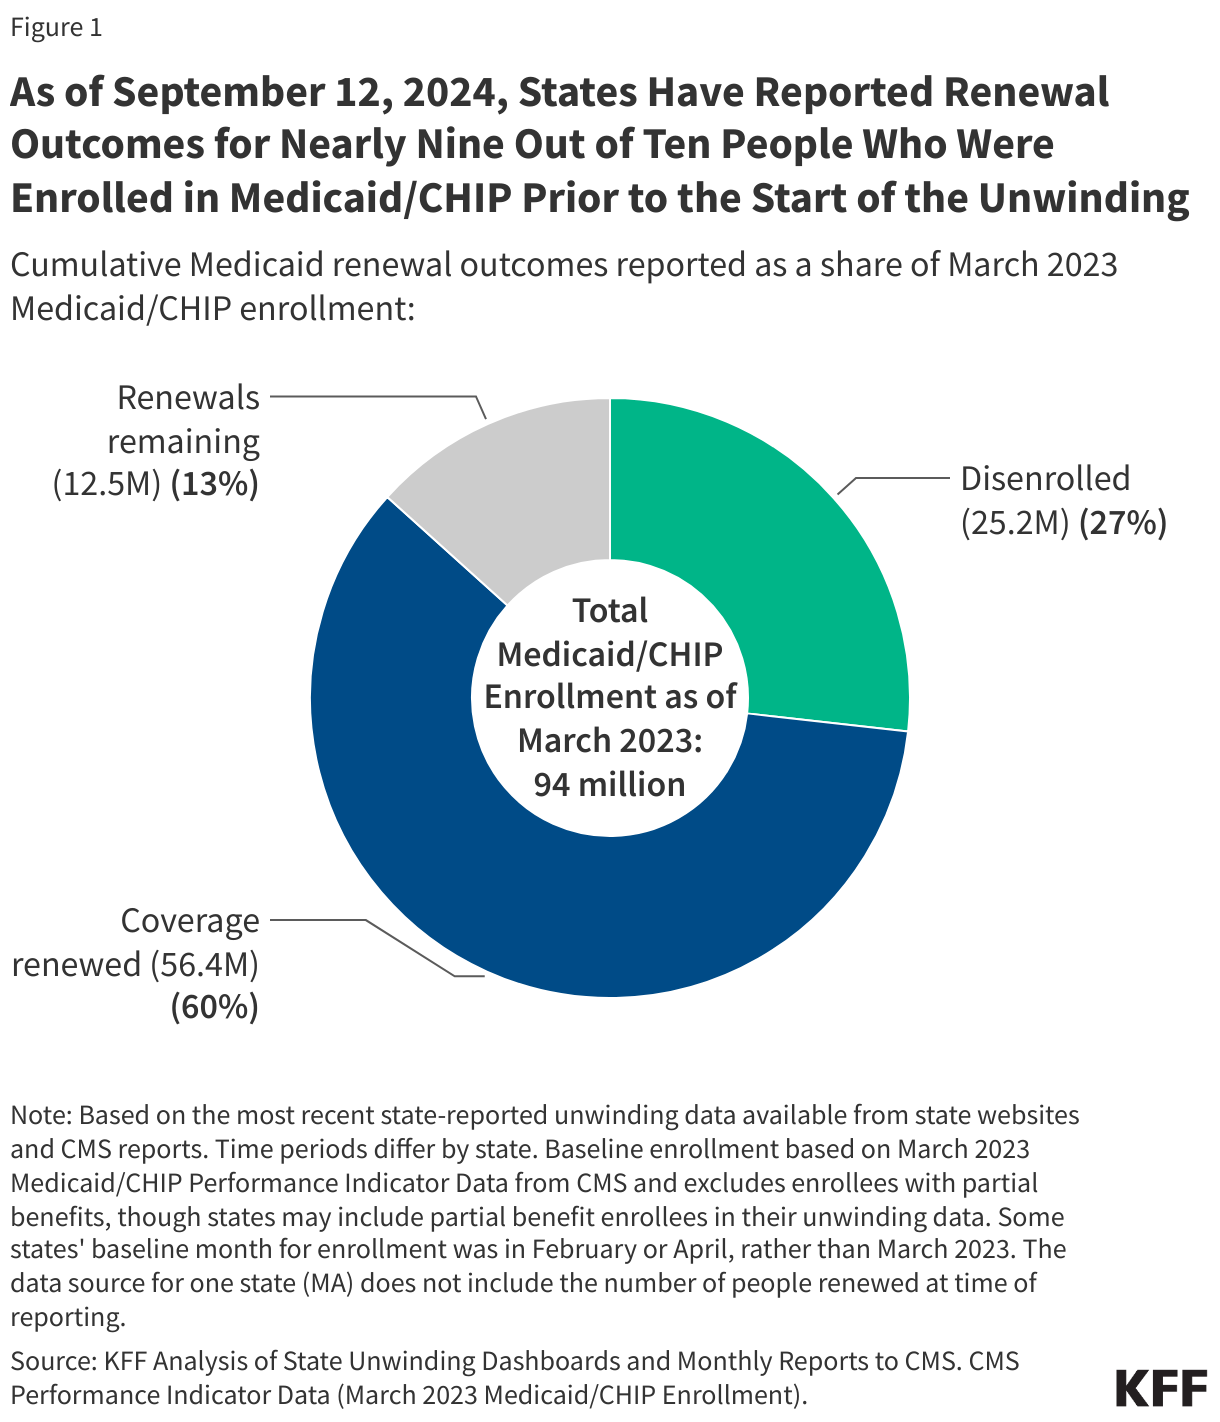
Though the acute phase of the Medicaid unwinding concluded for most states by late 2024, the operational data compiled up to September 12, 2024, offers critical insights into the resilience and administrative fragility of public health coverage systems. For nearly a year and a half, state health agencies were tasked with redetermining eligibility for more than 80 million people—the largest administrative undertaking in the history of the U.S. social safety net.
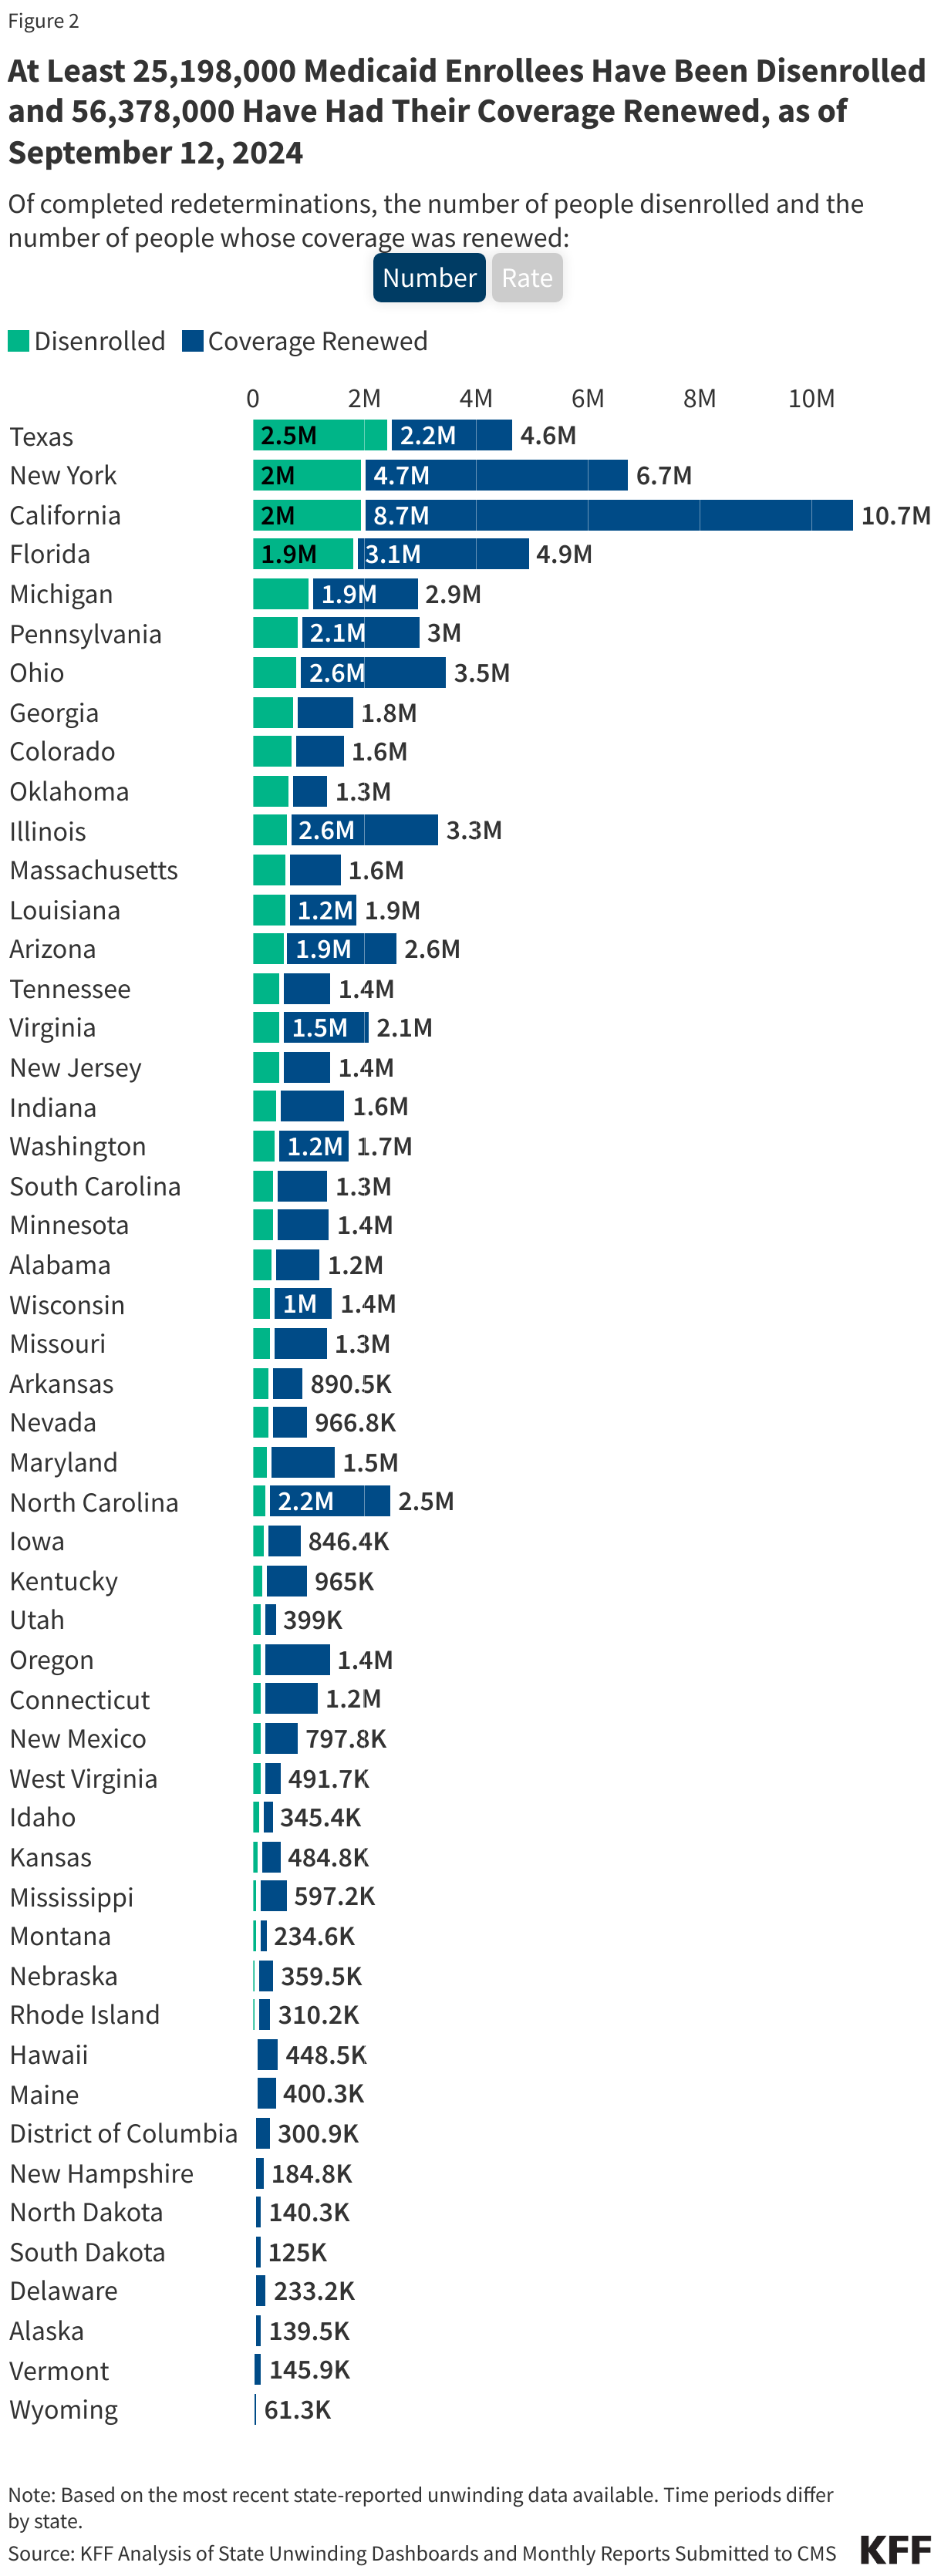
According to final and near-complete cumulative data compiled by KFF from state dashboards and CMS reporting, states completed renewal outcomes for nearly nine out of ten individuals who were enrolled in Medicaid or CHIP at the start of the unwinding. Out of those evaluated, at least 25,198,000 enrollees were successfully disenrolled, while 56,378,000 individuals had their coverage officially renewed.
The numbers reveal vast disparities in state performance and administrative efficiency. Disenrollment rates varied wildly across reporting jurisdictions, stretching from a high of 57% in Montana down to just 12% in North Carolina. These disparities were driven by differences in state-level outreach, the automation of data systems, and the aggressiveness of local eligibility processing.
The Crisis of Procedural Disenrollments
One of the most alarming revelations of the unwinding period was the staggering proportion of enrollees who lost health coverage not because they were found financially ineligible, but due to administrative red tape.
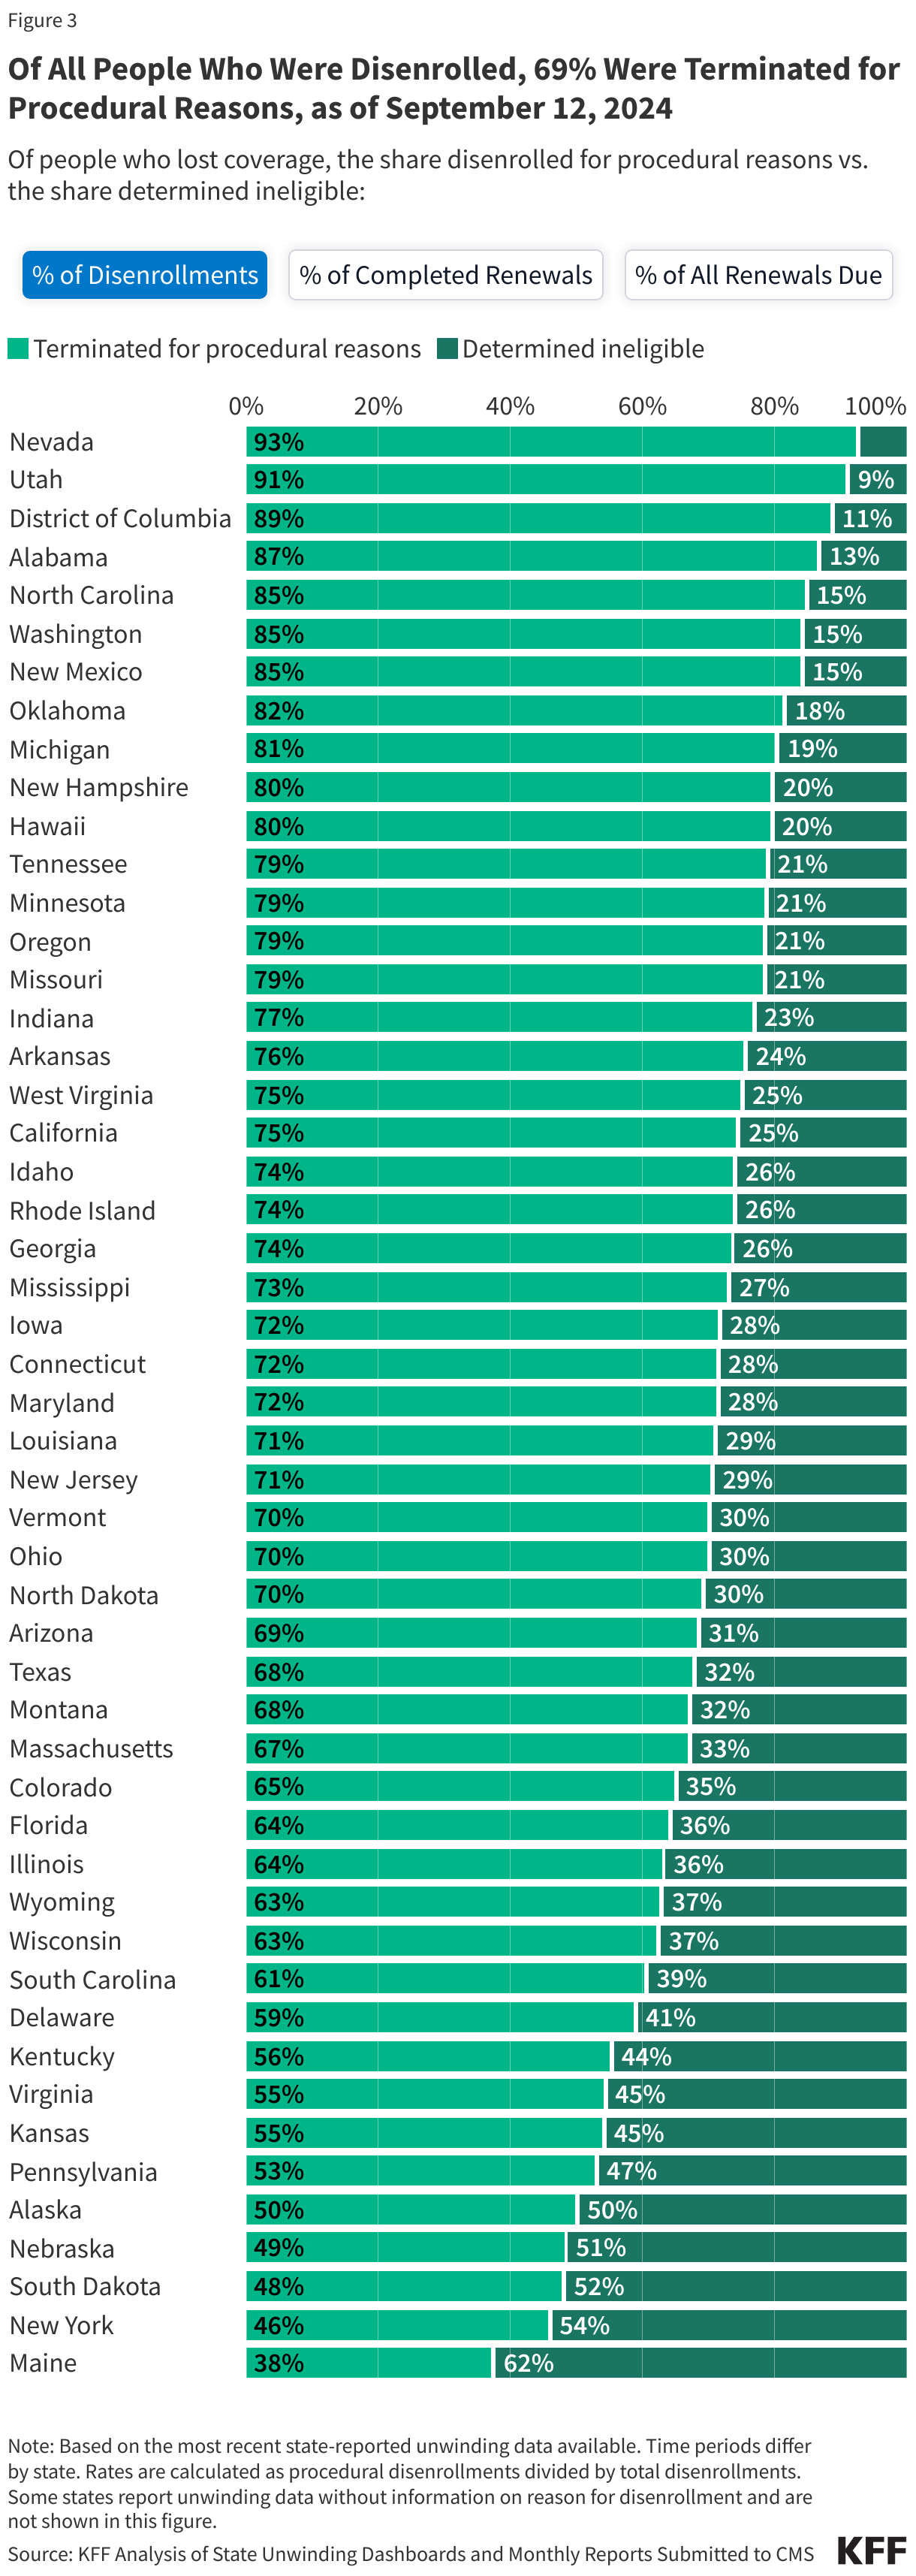
Of all the individuals who were disenrolled during the unwinding, a staggering 69% were terminated for procedural reasons. Procedural disenrollments occur when a state agency fails to receive the necessary renewal paperwork or documentation from an enrollee—frequently because renewal notices were mailed to outdated addresses, notices were difficult to comprehend, or processing backlogs overwhelmed state communication channels.
When measured against all completed renewals during the unwinding period, procedural terminations accounted for roughly 21% of all cases. When factoring in every renewal due—including those cases that remained indefinitely pending in bureaucratic limbo—procedural terminations accounted for approximately 20% of all cases.
States that utilized automated administrative renewals, known as ex parte renewals, fared significantly better at protecting eligible citizens from falling through the cracks. Overall, data shows that 61% of individuals who successfully retained their Medicaid coverage during the unwinding did so via ex parte processes, where state agencies leveraged existing electronic data sources (such as wage databases or SNAP records) to verify eligibility automatically without requiring the enrollee to fill out a single form.
Implications for the Future of Public Health Coverage
The lessons drawn from the post-pandemic unwinding period and the subsequent enrollment trends of 2026 carry profound implications for policymakers, healthcare providers, and low-income families.
First, the heavy reliance on procedural disenrollments underscores the ongoing vulnerability of safety-net populations to administrative friction. Millions of Americans—many of them children and working-class parents—temporarily or permanently lost access to essential medical, mental health, and preventative care simply because they could not successfully navigate complex renewal bureaucracy. While many of these individuals likely remained eligible for coverage, re-enrolling them often requires extensive navigation assistance from community health workers and enrollment brokers.
Second, as federal policy shifts toward stricter eligibility checks, such as the upcoming 2027 work requirements, state Medicaid agencies will face renewed pressure to modernize their data infrastructure. States that successfully implemented robust automated ex parte renewal systems during the unwinding demonstrated that administrative hurdles can be minimized. Conversely, states with rigid reporting structures risk amplifying coverage gaps.
Ultimately, tracking Medicaid and CHIP enrollment trends remains a vital barometer of economic stability and public health access in the United States. As the healthcare system adjusts to post-pandemic norms while preparing for the regulatory contraction mandated by the 2025 budget reconciliation law, ensuring transparent data reporting will be paramount for holding state and federal officials accountable to the millions of Americans who depend on public health coverage.
Related posts: